EFMODY Modified-release hard capsule Ref.[50004] Active ingredients: Hydrocortisone
Source: European Medicines Agency (EU) Revision Year: 2026 Publisher: Immedica Pharma AB, 113 63 Stockholm, Sweden
5.1. Pharmacodynamic properties
Pharmacotherapeutic group: Corticosteroids for systemic use; glucocorticoids
ATC code: H02AB09
Mechanism of action
Hydrocortisone is a glucocorticoid. Glucocorticoids have multiple effects in multiple tissues through actions on the intracellular steroid receptors.
Pharmacodynamic effects
Hydrocortisone is a glucocorticoid and the synthetic form of endogenously produced cortisol. Glucocorticoids are adrenocortical steroids, both naturally occurring and synthetic, which are readily absorbed from the gastro-intestinal tract. Cortisol is the principal corticosteroid secreted by the adrenal cortex. Naturally occurring glucocorticoids (hydrocortisone and cortisone), which also have salt-retaining properties, are used as replacement therapy in adrenocortical deficiency states. They are also used for their potent anti-inflammatory effects in disorders of many organ systems. Glucocorticoids cause profound and varied metabolic effects. In addition, they modify the body's immune responses to diverse stimuli.
Clinical efficacy and safety
CAH
A double blind double dummy study (DIUR-014) of 53 participants with CAH (21 hydroxylase deficiency) randomised participants to either twice daily Efmody or twice daily immediate release hydrocortisone (IRHC) after 4 weeks run in on 30 mg IRHC daily. At baseline (randomisation) 28.6% of participants allocated to the IRHC cohort were in biochemical control compared to 52.0% of participants allocated to Chronocort. Following randomisation participants had blinded titration of dosing at 3 visits with dose reductions (in 5 mg steps at each visit) conducted if participants had 17-OHP <300 ng/dL and A4 <150 ng/dL in men and <200 ng/dL in women. The difference between Chronocort and IRHC treatment in the proportion of participants in biochemical response was 84.0% vs 14.3% at Week 10 and 72.0% vs 17.9% at Week 16. After 28 weeks the study demonstrated that more participants were biochemical responders with Efmody treatment (40.0%) compared to IHRC treatment (14.3%) (p=0.015). Biochemical responders were defined as having a 0800hrs 17-OHP concentration ≤1200 ng/dL (36.4 nmol/L) plus a 0800hrs A4 concentration ≤150 ng/dL (5.2 nmol/L) for men or ≤200 ng/dL (7.0 nmol/L) for women plus a total daily dose of hydrocortisone after 28 weeks of randomized treatment of not more than 25 mg (if the participant was in biochemical control at baseline) or not more than 30 mg (if the participant was not in biochemical control at (baseline. Overall, participants had a lower mean daily dose following Efmody treatment (20.2 mg) compared to IRHC treatment (26.0 mg) (p<0.001).
An open label study (DIUR-005) in 122 participants with CAH (21-hydroxylase deficiency) randomised to Efmody or continuation of standard care with blinded titration of dose and regular overnight profiles failed to meet its primary endpoint of superiority in change from baseline to 24 weeks of the mean of the 24-hour standard deviation score (SDS) profile for 17-hydroxyprogesterone (17-OHP). The percentage of patients with controlled 09:00 hours 17-OHP (<36nmol/l) was 50% at baseline and at 24 weeks was 91% in the Efmody cohort and 71% in the standard therapy cohort. Efmody patients suffered no adrenal crises (compared to 3 in the control arm) and had fewer sick day episodes where increased dosing due to stress was required (26 vs 36 in the control arm) despite reporting more episodes of intercurrent infective or gastro-intestinal illness.
Figure 1. End of study geometric mean 24-hour profile of 17-OHP after 24 weeks intensive treatment with either Efmody (closed circles) or standard therapy (open circles):

A safety extension study of 91 patients with titration by investigators (DIUR-006) was characterised by dose reductions with median daily dose of Efmody at 18 months (n=50) being 20 mg (from a median baseline daily dose of 30 mg) with 17-OHP levels remaining in the clinically determined optimal range and androstenedione at or below the reference range for normal individual.
AI
A double-blind, double-dummy crossover study in fifty eight primary adrenal insufficiency participants compared the efficacy, safety and tolerability of twice daily Efmody and once-daily Plenadren over a treatment period of up to two months, with two 4-week treatment periods. Treatment order was randomised. At the end of 4 weeks treatment (periods 1 and 2), the median serum cortisol was higher at the 07:00 timepoint during Efmody treatment (417.0 nmol/L) compared to Plenadren treatment (6.04 nmol/L).
A profile plot of daytime salivary cortisone values from 7 to 22 hours clock time in different treatment groups is provided in Figure 2.
Figure 2. Profile Plot of Daytime Salivary Cortisone levels in IRHC, Plenadren and Efmody (Chronocort) - treated subjects in Study DIUR-016-AI with overlaid Normative Data:
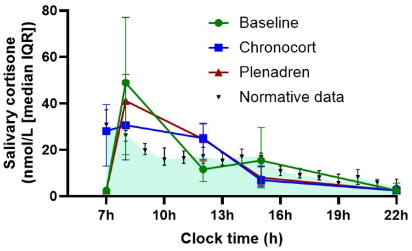
Shaded area represents normative data from 14 healthy adults
IRHC: immediate-release hydrocortisone (Baseline)
5.2. Pharmacokinetic properties
Absorption
Following a single oral administration in fasted dexamethasone-suppressed healthy adults, the rate of absorption of hydrocortisone from Efmody 20 mg was delayed and reduced compared to immediate release hydrocortisone tablets 20 mg, as reflected by a lower Cmax and a significantly longer Tmax for Efmody (median Tmax for serum cortisol of 4.5 hours and 0.88 hours for Efmody and hydrocortisone tablets respectively). Efmody appeared to be more bioavailable relative to immediate release hydrocortisone tablets, with overall exposure to serum cortisol and derived free cortisol approximately 19% and 13% higher respectively for Efmody.
In the same population, food (high fat meal started 30 minutes before dosing) was found to delay and reduce the rate of absorption of hydrocortisone from Efmody 20 mg, as reflected by a longer Tmax (median Tmax for serum cortisol of 6.75 hours and 4.5 hours for fed and fasted subjects respectively) and lower Cmax (reduced by approximately 20% in fed subjects). Overall exposure appeared similar in fed and fasted subjects (90% confidence intervals for the fed/fasted ratio of the geometric least square mean of AUC0-t and AUC0-inf were within 80-125%). This effect is therefore not considered clinically significant.
Distribution
At least 90% of circulating hydrocortisone is reversibly bound to protein.
The binding is accounted for by two protein fractions. One, corticosteroid-binding globulin is a glycoprotein; the other is albumin.
Biotransformation
Hydrocortisone is metabolised in the liver and most body tissues to hydrogenated and degraded forms such as tetrahydrocortisone and tetrahydrocortisol which are excreted in the urine, mainly conjugated as glucuronides, together with a very small proportion of unchanged hydrocortisone. Hydrocortisone is both metabolised by and a regulator of CYP3A4.
Elimination
In the fasted dexamethasone-suppressed healthy adult population described above, terminal elimination half-life values were similar for Efmody and hydrocortisone tablets (geometric mean t1/2 for serum cortisol of 1.38 hours and 1.40 hours respectively). Clearance appeared higher for hydrocortisone tablets relative to Efmody (geometric mean CL/F for serum cortisol of 22.24 L/h and 18.48 L/h respectively).
Renal impairment
No studies have been conducted in patients with renal impairment.
Hepatic impairment
No studies have been conducted in patients with hepatic impairment.
Paediatric population
The pharmacokinetics of Efmody have not been studied in the paediatric population.
5.3. Preclinical safety data
Administration of corticosteroids to pregnant animals can cause abnormalities of fetal development including cleft palate, intrauterine growth retardation and effects on brain growth and development.
© All content on this website, including data entry, data processing, decision support tools, "RxReasoner" logo and graphics, is the intellectual property of RxReasoner and is protected by copyright laws. Unauthorized reproduction or distribution of any part of this content without explicit written permission from RxReasoner is strictly prohibited. Any third-party content used on this site is acknowledged and utilized under fair use principles.